From the perspective of teens, TikTok is a major new outlet for self-expression, one proudly home to the silly, the loud and the weird.
Read More
Views: 1

From the perspective of teens, TikTok is a major new outlet for self-expression, one proudly home to the silly, the loud and the weird.
Read More
Views: 1

U.S. regulators have proposed fining the four major U.S. phone companies more than $200 million combined for improperly disclosing customers’ real-time location to other companies.
Read More
Views: 1

Many children with autism face developmental delays, including communication and behavioral challenges and difficulties with social interaction. This makes learning new skills a major challenge, especially in traditional school environments.
Read More
Views: 0

Vaccination, screening, treatment and palliative care are the key interventions of WHO’s Draft Global Strategy towards the Elimination of Cervical Cancer as a Public Health Problem,
the fourth most common cancer in women.
On World Cancer Day, new estimates show that this strategy could save more than 62 million girls and women from a cervical cancer death and prevent 74 million cases within the next 100 years – but only if these interventions are used effectively
together.
These estimates, published by the WHO Cervical Cancer Elimination Modelling Consortium (CCEMC) in The Lancet, are based on the draft strategy’s targets to achieve a global coverage of 90% vaccination, 70% screening and 90% treatment by 2030.

Developed by Member States, UN agencies and other partners, the draft global strategy seeks to redress the unequal burden of cervical cancer around the world. Nine in 10 cervical cancer deaths occur in low and lower-middle-income countries, where
women lack access to health services.
As Dr Tedros Adhanom Ghebreyesus, WHO’s Director-General has said, “It doesn’t have to be this way. Cervical cancer
is one of the most preventable and treatable forms of cancer, as long as it is detected early and managed effectively.”
This new analysis compares the impact of vaccination, screening and treatment of cervical pre-cancer lesions as single or combined interventions. Focusing on 78 countries where cervical cancer mortality is highest, the results clearly show that no
single intervention will be sufficient to reduce levels of cervical cancer in the next 100 years to below the elimination target of 4 cases per 100,000 women per year.
Acting immediately on all three fronts is crucial.
Vaccinating girls against cancer-causing types of human papillomavirus (HPV) before the age of 15 is the foundation for bringing every country’s incidence rate of cervical cancer down to the agreed elimination level.
Right now, however, vaccination is not enough. As a single strategy, vaccination targets would only deliver a 0.1% reduction in cervical cancer mortality by 2030. Scaling up screening and treatment of cervical pre-cancer lesions at the same time would
reduce mortality by more than one third, or 300,000 deaths, in the same period.
The evidence shows that when all adult women are screened for cervical cancer at least twice, at ages 35 and 45, abnormalities are more likely to be detected before they become cancerous. When cancer has developed, screening increases a women’s
likelihood of early and successful treatment, as well as palliative care if recovery is no longer an option.
Meeting these triple-intervention targets would be a major contribution to target 3.4 of the UN Sustainable Development Goals (SDGs), a one-third reduction in premature mortality from non-communicable diseases by 2030.
WHO’s global strategy towards eliminating cervical cancer aims to set the world on the right track by 2030, but it is just the beginning.
At this pace, global elimination of cervical cancer is not predicted until 2120.
While high HPV vaccination coverage is the primary prevention intervention, ensuring every woman has two cervical screenings in her life would accelerate elimination by 11 – 31 years, depending on the country.
If no action is taken, cervical cancer deaths will rise almost 50% by 2030. Approval of the draft global strategy at the WHO World Health Assembly in 2020, and investment in mechanisms to deliver it, is vital.
As the new World Cancer Report shows, only 18% of countries that currently provide screening for cervical cancer reached the recommended target of more than 70% coverage. An estimated 55% of low-income countries that reported offering
cervical cancer screening generally lack accessible radiotherapy or surgery services.
Elimination of cervical cancer is possible within the lifetime of today’s youngest girls, but the clock starts now and every intervention counts.

Read More
https://www.who.int/news-room/detail/04-02-2020-to-eliminate-cervical-cancer-in-the-next-100-years
Views: 0
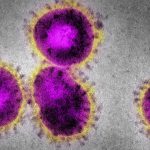
Leading health experts from around the world have been meeting at the World Health Organization’s Geneva headquarters to assess the current level of knowledge about the new COVID-19 disease, identify gaps and work together to accelerate and fund priority research needed to help stop this outbreak and prepare for any future outbreaks.
The 2-day forum was convened in line with the WHO R&D Blueprint – a strategy for developing drugs and vaccines before epidemics, and accelerating research and development while they are occurring.
“This outbreak is a test of solidarity — political, financial and scientific. We need to come together to fight a common enemy that does not respect borders, ensure that we have the resources necessary to bring this outbreak to an end and bring our best science to the forefront to find shared answers to shared problems. Research is an integral part of the outbreak response,” said WHO Director-General Dr Tedros Adhanom Ghebreyesus. “I appreciate the positive response of the research community to join us at short notice and come up with concrete plans and commitment to work together.”
The meeting, hosted in collaboration with GloPID-R (the Global Research Collaboration for Infectious Disease Preparedness) brought together major research funders and over 300 scientists and researchers from a large variety of disciplines. They discussed all aspects of the outbreak and ways to control it including:
“This meeting allowed us to identify the urgent priorities for research. As a group of funders we will continue to mobilize, coordinate and align our funding to enable the research needed to tackle this crisis and stop the outbreak, in partnership with WHO,” said Professor Yazdan Yazdanpanah, chair of GloPID-R. “Equitable access – making sure we share data and reach those most in need, in particular those in lower and middle-income countries, is fundamental to this work which must be guided by ethical considerations at all times.”
During the meeting, the more than 300 scientists and researchers participating both in person and virtually agreed on a set of global research priorities. They also outlined mechanisms for continuing scientific interactions and collaborations beyond the meeting which will be coordinated and facilitated by WHO. They worked with research funders to determine how necessary resources can be mobilized so that critical research can start immediately.
The deliberations will form the basis of a research and innovation roadmap charting all the research needed and this will be used by researchers and funders to accelerate the research response.
GloPID-R is a global alliance of international research funding organizations investing in preparedness and response to epidemics.

Read More
https://www.who.int/news-room/detail/12-02-2020-world-experts-and-funders-set-priorities-for-covid-19-research
Views: 0

Government ministers and senior officials from over 100 countries will meet in Stockholm, Sweden from 19-20 February to discuss new steps to halve road traffic deaths and injuries by 2030, in line with global targets agreed in the United Nations Sustainable Development Goals (SDGs).
“The fact that an estimated 1.35 million lives are lost every year due to road traffic collisions is an outrage. It is an unacceptable price to pay for mobility,” said Dr Tedros Adhanom Ghebreyesus, Director-General at the World Health Organization (WHO).
Road traffic injuries are now the leading cause of death for children and young adults aged 5 to 29 years, according to WHO’s most recent Global status report on road safety.
More than half of all road traffic deaths occur among pedestrians, cyclists and motorcyclists. The risk of a road traffic death remains three times higher in low-income countries than in high-income countries. Moreover, as many as 50 million people experience non-fatal road injuries, which impose human suffering and major economic losses.
“Most road traffic deaths and injuries can be prevented, using tried and tested strategies,” added Dr Tedros. “This conference is an opportunity for the world to embrace a new agenda to radically reduce the number of lives lost on our roads and re-think how we can provide access to safe, affordable, accessible and sustainable transport systems for all.”
Progress in road safety
Many countries have already made progress through effective road safety management and focusing on better legislation and enforcement around key risks such as speeding; drinking and driving, and failing to use seatbelts. They have also improved infrastructure through measures such as safer sidewalks and dedicated lanes for cyclists; implemented vehicle standards such as those that mandate advanced braking and electronic stability control; and enhanced post-crash care.
Improvements have occurred when a number of sectors have been involved – including transport, health, urban planning and law enforcement, among others. Success has also depended mainly on strong leadership and political will at the highest level of government and in close collaboration with civil society and the private sector.
The Stockholm Declaration
Hosted by the Government of Sweden in collaboration with WHO, the 3rd Global Ministerial Conference on Road Safety offers delegates an opportunity to share successes and lessons learned, chart future strategic directions for global road safety, and define ways to fast-track progress around proven strategies to save lives.
The Stockholm Declaration will be presented as the final outcome document of the Ministerial Conference calling for strong political will and international cooperation as well as partnerships across many sectors of society. The Declaration will lay out key recommendations for accelerated action to drive progress towards halving global road traffic deaths and injuries by 2030.
Beyond preventing human suffering and major economic losses, addressing road traffic deaths and injuries has positive impact across all aspects of society and development ─ including those linked to environment, climate change, education, employment, energy, poverty, human rights and equality ─ as outlined in the SDG targets.
Note to editors:
Road safety is reflected in the SDGs agreed in 2015, with two dedicated targets: (a) 3.6 aimed at preventing road traffic deaths and injuries and (b) 11.2 providing access to safe, affordable, accessible and sustainable transport systems for all.
Achieving these targets would lead to increases in walking, cycling and using public transport, in other words, those modes of transport which impact most favorably on noncommunicable diseases like heart and lung diseases, cancer and diabetes. It would also contribute to reducing environmental risks, such as air and noise pollution, and steering sustainable urbanization, with less congestion and universal access to safe, inclusive and green public spaces.

Read More
https://www.who.int/news-room/detail/07-02-2020-ministers-to-agree-new-global-road-safety-agenda-to-2030
Views: 0

Female genital mutilation (FGM) exacts a crippling economic as well as human cost, according to World Health Organization (WHO).
“FGM is not only a catastrophic abuse of human rights that significantly harms the physical and mental health of millions of girls and women; it is also a drain on a country’s vital economic resources,” said Dr Ian Askew, Director of WHO’s Department of Sexual and Reproductive Health and Research. “More investment is urgently needed to stop FGM and end the suffering it inflicts.”
New modelling reveals that the total costs of treating the health impacts of FGM would amount to USD 1.4 billion globally per year, if all resulting medical needs were addressed. For individual countries, these costs would near 10% of their entire yearly expenditure on health on average; in some countries, this figure rises to as much as 30%.
The interactive modelling tool that generated these data was launched on the International Day of Zero Tolerance for Female Genital Mutilation.
Women and girls living with FGM face serious risks to their health and well-being. These include immediate consequences after being cut, such as infections, bleeding or psychological trauma, as well as chronic health conditions that can occur throughout life.
Women who have undergone the procedure are more likely to experience life-threatening complications during childbirth. They may face mental health disorders or suffer chronic infections. They may also have pain or problems when they menstruate, urinate or have sexual intercourse.
All of these conditions warrant much-needed medical attention and care.
“High healthcare costs for countries mount because of the tragic personal impacts on women and girls. Governments have a moral responsibility to help end this harmful practice,” says Dr Prosper Tumusiime, Acting Director for Universal Health Coverage and the Life Course in the African Regional Office of WHO. “FGM hurts girls, imposes lifelong health risks on the women they become, and strains the healthcare systems that need to treat them.”
Using data from 27 high-prevalence countries, the Cost Calculator demonstrates clear economic benefits from ending FGM. If it were abandoned now, it shows that the associated savings in health costs would be more than 60% by 2050.
In contrast, if no action is taken, it is estimated that these costs will soar by 50% over the same time period, as populations grow and as more girls undergo the procedure.
Since 1997, great efforts have been made to end FGM, through work within communities, research, and changes in legislation and policy. 26 countries in Africa and the Middle East now explicitly legislate against FGM, as well as 33 other countries with migrant populations from FGM-practicing countries.
WHO is also working with countries to raise awareness of the harmful impacts of the practice among their health workers, and to engage them in prevention efforts.
“Many countries and communities are showing that abandoning female genital mutilation is possible,” states Dr Christina Pallitto, scientist at WHO. “If countries invest to end female genital mutilation, they can prevent their girls from undergoing this harmful practice and promote the health, rights and well-being of women and girls.”
Female genital mutilation is internationally recognized as a human rights violation. It has no medical benefits and causes only harm. WHO’s position is that FGM must never be carried out.
The FGM Cost Calculator will be available here, as of 00:30 CET 6 February 2020:
www.who.int/news-room/detail/06-02-2020-economic-cost-of-female-genital-mutilation
FGM includes procedures that intentionally alter or cause injury to the female genital organs for non-medical reasons. More than 200 million girls and women alive today are estimated to have undergone the practice across 30 countries in Africa, the Middle East and Asia where FGM is concentrated.
FGM is mostly carried out on young girls between infancy and 15 years of age.
The WHO FGM Cost Calculator shows the economic cost of treating the health complications caused by FGM across 27 high-prevalence countries. These costs were calculated using the WHO One Health tool and other available scientific evidence.
Users of the tool can calculate costs by country in a ‘business as usual’ scenario; a scenario of partial abandonment of FGM, and full abandonment of FGM over a 30-year period. In addition, the distribution of costs by different types of health complications is presented by country.
The tool does not consider other indirect costs that hit families and communities, or the socio-economic impacts of the practice, which would be significantly higher still.
The 27 countries modelled include Benin, Burkina Faso, Central African Republic, Còte d’Ivoire, Cameroon, Chad, Djibouti, Egypt, Eritrea, Ethiopia, Ghana, Guinea, Gambia, Guinea-Bissau, Iraq, Kenya, Mali, Mauritania, Niger, Nigeria, Soudan, Senegal, Sierra Leone, Somalia, Togo, United Republic of Tanzania, Yemen.

Read More
https://www.who.int/news-room/detail/06-02-2020-female-genital-mutilation-hurts-women-and-economies
Views: 0

Major League Baseball players have become overwhelmingly overweight and obese during the last quarter century, say health researchers.
David E. Conroy, Penn State professor of kinesiology, and colleagues looked at 145 years of data on professional baseball players’ body mass. The researchers found that the athletes’ weight held steady for over 100 years, with the majority of them weighing in at what is considered “normal,” – i.e., with a body mass index (BMI) between 18.5 and 24.9.
However, around 1991 the average player’s BMI began to rise, and over the last 25 years nearly 80 percent of players fall into the overweight or obese category with a BMI above 25. Obesity in the general U.S. population began to rise in the mid-1970s, according to the Centers for Disease Control and Prevention.
“Research exists that shows how having extra weight can help with certain aspects of baseball,” said Conroy, also professor of human development and family studies. “The more force a batter can put into the ball, the further it will travel.”
Views: 0

In a major step to curb eavesdroppers from tapping into users’ web browsing habits, Mozilla today launched a major security initiative for all Firefox users in the United States.
Views: 0